

The most expensive dosing mistake is inheriting a number nobody ever checked. Three of the peptide dosing numbers repeated most confidently online could not be traced to any document containing them: the 20-day shelf life for a mixed vial, the cycling calendar of 12 weeks on and 4 to 6 weeks off, and the claim that 80% of people measure under 13mm from skin to muscle. The arithmetic is still worth getting right, and the FDA has documented patients receiving 5 to 20 times more than an intended dose [[2]]. But in the FDA's adverse event reports on compounded GLP-1 drugs, the recorded harm clusters upstream of the syringe: compounded products showed roughly 49 times the reporting odds for preparation errors and 19 times for contamination, against 0.24 for the patient's own dosing errors [[1]].
The most expensive dosing mistake is inheriting a number nobody ever checked. Three of the numbers repeated most confidently in peptide forums and vendor dosing guides do not survive a check against their sources. The 20-day shelf life for a mixed peptide vial is usually attributed to a bacteriostatic water label, and that label explicitly declines to set any such period 3. The cycling calendar descends from a 2003 rat study that reported a dosing-pattern effect over 7 days and no human schedule at all 4. For the figure that 80% of people measure 13mm or less from skin to muscle, we could not find any document containing it, while ultrasound measurement in 341 adults gives far more specific numbers 5. So the seven rules below are sorted by what each one rests on, not by how often it gets repeated.
The seven rules, and what each one rests on
Read the third column first. Sourced means the rule and the number both hold up. Partly sourced means the mechanism is real and the specific claim attached to it has never been measured. No document found means the number could not be traced to anything containing it.
| Rule as it is usually stated | What it rests on | Survives a source check? |
|---|---|---|
| Concentration math errors are the main danger | The FDA's own alert, which documents a provider writing 25 units for an intended 0.25 mg, and patients self-administering 5 to 20 times more than the intended dose 2 | Sourced. Real, documented, and smaller in the compounded GLP-1 reporting data than product preparation problems 1 |
| Never shake the vial, and foam means the peptide is ruined | A formulation study showing that agitation speeds the clumping of protein at the air-water boundary, run on a growth-factor protein with added detergent and not on a peptide vial 9 | Partly sourced. The mechanism is real. Nobody has measured whether a foamy peptide vial is ruined |
| Bacteriostatic water keeps a mixed peptide stable for 20 days, sterile water for 3 to 5 | The bacteriostatic water label, which sets no such period and says not to store mixed drug solutions unless the maker of that drug directs otherwise 3 | No document found for either number. Both are inherited |
| Keep powder frozen, keep mixed vials cold and dark | General protein chemistry plus each manufacturer's own storage line. No published stability study of BPC-157, ipamorelin or CJC-1295 in solution was found | Partly sourced. Sensible handling, with no peptide-specific number behind the usual figures |
| Continuous use downregulates your receptors, so cycle off on a calendar | One 7-day infusion study in growth-hormone-deficient rats. Continuous infusion did suppress spontaneous growth hormone pulse amplitude, and the paper excluded pituitary desensitization and hypothalamic receptor downregulation as the reason, finding a rise in the body's own brake on growth hormone instead 4 | Effect partly sourced, mechanism and calendar not. No human trial tests the on-and-off schedules these guides repeat |
| A long needle at 90 degrees lands in muscle, because 80% of people are under 13mm skin to muscle | No document containing the 80% figure could be found. Ultrasound in 341 adults gives median skin-to-muscle distances of 10.9mm at the thigh to 16.9mm at the buttock 5 | Rule sourced, number not. An 8mm needle at the abdomen carried about a 1 in 10 estimated risk, not reliable muscle entry |
| A slow-metabolizer genotype changes your peptide dose | Nothing. Peptides are cleared by peptidases, while liver enzyme genotype governs small-molecule drugs 7 | Premise is wrong. Peptides are not cleared by liver enzymes |
1. Concentration math errors are documented, and the FDA case is on the record
The milligram-to-unit confusion story is told everywhere without a source, and it has a real one. The FDA's compounding alert describes a specific case in these words.
One provider intended to dose 0.25 milligrams (5 units), but prescribed 25 units instead, leading to a patient receiving five times the intended dose and experiencing severe vomiting.FDA, alert on dosing errors with compounded injectable semaglutide, updated 26 July 2024 [[2]]
The same FDA page describes patients self-administering 5 to 20 times more than the intended dose. The mechanism is the syringe. A U-100 insulin syringe is marked in units where each unit is one hundredth of a milliliter, so the numbers printed on the barrel have no fixed relationship to milligrams of peptide until someone works out how much water went into the vial. Our reconstitution guide makes the same point with a worked example: put 1mL into a 5mg vial and a 250 mcg dose lands at "exactly 5 units, which on most syringes sits between major tick marks. One unit off in either direction is a 20% dosing error."
The arithmetic itself belongs to how to reconstitute peptides, which owns the milligram-per-milliliter worked examples and the calculator. Each compound's published numbers live on its own page: BPC-157, TB-500, sermorelin, semax and GHRP-2. If none of that is familiar yet, peptides for beginners is the on-ramp.
2. Shaking the vial is partly sourced, and the foam claim is not measured
The mechanism behind the rule is real and published. A 2013 formulation study used interfacial shear rheology, a technique for measuring what happens to a liquid surface under stress, and found that agitation accelerated the formation of protein particles at the air-water boundary. Adding polysorbate 80, a detergent used in injectable formulations, substantially inhibited that agitation-induced clumping 9.
That study has two limits. It was run on a growth-factor protein in a designed formulation, not on a vial of a research peptide, and whether it transfers depends on what else is in the vial, including whether any such detergent is present. No study was found that tested hand-shaking a peptide vial and measured the result. Verdict: handle the vial gently, because it costs nothing. Stop telling people foam means the vial is dead, because nobody has checked. Clumped protein matters for a second reason as well, since aggregates are one of the recognized drivers of an immune response to an injected peptide, which has its own page at anti-drug antibodies. Sterile technique and site rotation are covered on the peptide injection hygiene guide.
3. The 20-day shelf life for bacteriostatic water has no source
Bacteriostatic Water for Injection is water for injection with 0.9% (9 mg/mL) or 1.1% (11 mg/mL) benzyl alcohol added as a preservative that holds back microbial growth, supplied in a multiple-dose container designed to be entered more than once 3. On the question everyone reaches for it to answer, how long whatever you dissolve in it stays good, the label declines to answer.
Do not store reconstituted solutions of drugs for injection unless otherwise directed by the manufacturer of the solute.Bacteriostatic Water for Injection, USP prescribing information [[3]]
That single sentence carries the whole correction. An in-use discard date is set by the maker of the drug being dissolved, not by the water. A research peptide has no manufacturer of the solute issuing such a direction, so there is no established discard period to inherit. The 20-day figure appears nowhere on this label, and the 3 to 5 day figure for sterile water could not be traced to any document either.
Bacteriostatic water and sterile water, on the one question people ask them
4. Cold and dark storage is sensible, and no discard date has been established for a research peptide
Water, oxygen, heat and light all take a peptide apart in solution, so cold, dark and dry is uncontroversial handling that costs nothing. The number bolted onto it is the problem.
No published stability study of BPC-157, ipamorelin or CJC-1295 in solution was found, so the days-in-the-fridge figures circulating for these compounds are not measurements of these compounds. Handling matters, the direction of the effect is known, and the expiry date is not.
With no number to rely on, what is left is ordinary care. Write the mixing date on the vial, keep it cold and out of the light, keep the window short, and treat a solution that has gone cloudy, discolored or particulate as a reason to discard it instead of drawing from it. A specific product's in-use period is a question for a clinician or pharmacist, and general handling is covered on the how to reconstitute peptides.
5. The cycling calendar rests on a rat study that reported something narrower
The claim that continuous use of growth hormone secretagogues downregulates the receptor is the most confidently repeated statement in these guides, and the study it descends from is narrower than the retelling. Thompson and colleagues, writing in Endocrinology in 2003, infused ghrelin or GHRP-6 into moderately growth-hormone-deficient rats for 7 days, either in bursts every 3 hours or continuously 4. Continuous infusion did suppress the amplitude of the animals' own growth hormone pulses. What it did not do is what the rule says it does.
The reduction in GH secretion seen with continuous GHS-R activation was not associated with a desensitization of the pituitary to GH-releasing factor or to down-regulation of hypothalamic GHS-R mRNA expression.Thompson NM et al., Endocrinology 2003, on 7-day continuous infusion in growth-hormone-deficient rats [[4]]
What continuous stimulation did in growth-hormone-deficient rats
So the pattern finding is genuine, and so is the drop in growth hormone under continuous delivery. What does not follow from it is a calendar. No human trial has tested the on-and-off schedules these guides repeat for growth hormone secretagogues, including 12 weeks on with a 4 to 6 week washout and 5 days on with 2 days off. Our own cycling page says the same about the most common version of the rule: "The '8 weeks on, 4 weeks off' rule has no clinical trial behind it. It is practitioner convention extrapolated from receptor biology theory." Which compounds are cycled and on what evidence is argued there, on the peptide cycling protocol, and the receptor reset question has its own page at the growth hormone receptor reset timeline.
One thing this section is not. Showing that the calendar has no trial behind it is not evidence that uninterrupted use is safe. BPC-157, ipamorelin and CJC-1295 have no human safety data at any duration, and the open questions about continuous growth hormone secretagogue exposure are sustained IGF-1 elevation, effects on glucose and insulin sensitivity, and fluid retention. None of those has been measured in people taking these compounds, which is a reason for caution and not a schedule.
6. Needle length matters, and the 13mm figure attached to it is not the measured one
The rule is right and the number usually quoted for it cannot be found. Real measurement exists: ultrasound in 341 adults recorded median skin-to-muscle distances ranging from 10.9mm at the thigh to 16.9mm at the buttock, and the authors modeled how often a needle at 90 degrees without a pinched skin fold would reach muscle 5.
| Needle and technique | Estimated chance of reaching muscle at the abdomen | At the thigh | Source |
|---|---|---|---|
| 4mm at 90 degrees, no pinched fold | 0.1% | 1.6% | Ultrasound in 341 adults 5 |
| 8mm at 90 degrees, no pinched fold | 9.7% | 25% | Ultrasound in 341 adults 5 |
About 1 in 10 at the abdomen with an 8mm needle is a meaningful risk and a long way from the claim that a 16mm needle reliably enters muscle. The practical consequence of landing in muscle is a faster, higher peak and a sharper fall than an injection under the skin produces, which makes a protocol harder to judge from one week to the next. Why the route a peptide takes changes how much of it reaches the blood, and how fast, is covered on oral peptide bioavailability.
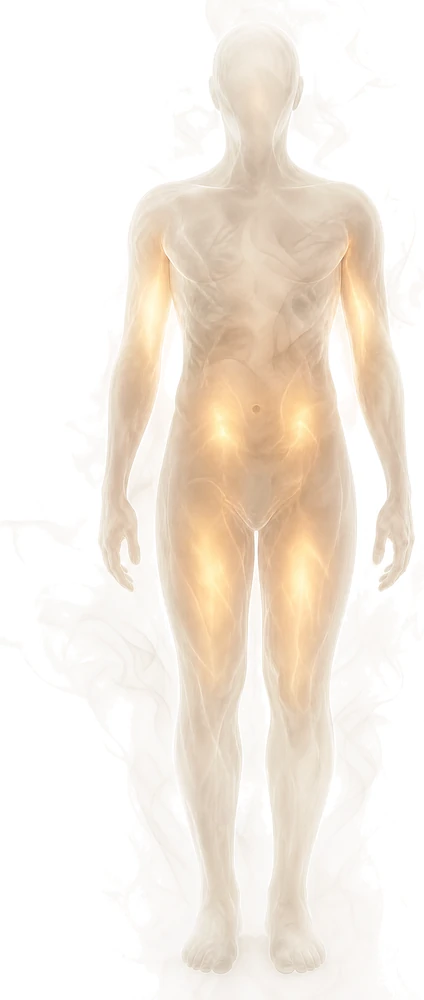
Subcutaneous sites
- AbdomenThe usual first choice. Stay roughly two finger-widths clear of the navel.
- Front or outer thighEasy to reach and easy to see what you are doing.
- Back of the upper armThe fleshy part at the back. Awkward to self-inject.
7. Liver enzyme genotype does not set a peptide dose
Two people can run the same protocol at the same dose for the same number of weeks and get different results, and the explanation reached for most often is a liver enzyme genotype, usually written as CYP3A4 or CYP2D6 status. That explanation fails on the mechanism. Those enzymes are the liver's machinery for small-molecule drugs such as statins and many antidepressants. Peptides are short chains of amino acids, and the body takes them apart with peptidases, mostly in blood, kidney and tissue. A slow-metabolizer genotype changes how long a statin lingers. It has no bearing on a peptide, because the two are cleared by different machinery.
The genetic evidence is more interesting than a flat null, and it points the same way. A study of real-world data from 8,118 patients taking quetiapine, an antipsychotic that genuinely is cleared by liver enzymes, tested both families of variant and found them doing different things.
A significantly higher NDQ C:D ratio was observed for CYP2D6 intermediate (+7%, P = .012) and poor (+17%, P = .001) compared to normal metabolizers. No effects of CYP3A4*22 and CYP3A5*1 allele variants were observed.
Read both halves. The CYP3A variants did nothing to exposure. The reduced-function CYP2D6 variants did, raising levels of the drug's active metabolite, and the authors concluded that women aged 65 and over who carry them have the highest risk of dose-dependent side effects 7. So liver enzyme genotype demonstrably matters for some small-molecule medicines, and anyone taking one should treat the pharmacogenetic guidance for that drug seriously. It is still irrelevant to a peptide, for the plain reason that a peptide never enters that pathway: there is no dose adjustment to calculate and no exposure multiple to correct for. Separately, consumer DNA array data cannot resolve CYP2D6, CYP3A4, CYP1A2 or CYP2E1, which is why PeptidesDNA does not report them and never claims to test them.
What the FDA safety data records
A 2026 pharmacovigilance analysis, meaning a study of adverse event reports and not a trial, pulled 81,078 GLP-1 reports from the FDA's adverse event reporting system between 2018 and 2024, of which 707 involved compounded products. Against the rest, compounded products showed reporting odds ratios of 48.92 [12.63, 189.6] for preparation errors, 19.00 [4.24, 85.03] for contamination, 8.51 [5.17, 14.0] for compounding or manufacturing problems and 2.35 [1.94, 2.83] for hospitalization, and lower odds for administration errors at 0.29 [0.16, 0.53] and for the patient's own dosing errors at 0.24 [0.17, 0.32] 1. The wide interval on preparation errors reflects how few such reports exist, so the direction is informative and the magnitude is not. It is a disproportionality signal, not an incidence rate, and it does not say dosing errors are rare. The FDA case reports quoted earlier show they are not 2.
The same study found more than medication errors. Compounded products also showed higher reporting odds for suicidality (6.34 [4.32, 8.99]), cholecystitis (3.39 [1.61, 6.31]) and abdominal pain (2.84 [2.29, 3.49]), and the authors state plainly that the study was not designed to show a cause-and-effect relationship 1. On volume, the FDA's own page reports 990 adverse event reports for compounded semaglutide and more than 730 for compounded tirzepatide as of 31 May 2026. Those are cumulative totals, not an annual count, and they refer to compounded versions that are not FDA-approved products and are not reviewed for safety, effectiveness or quality 8.
Those last two numbers are not a contradiction. The vials held more semaglutide than the label promised and a great deal of other material besides, so what any given draw delivered could not be worked out from the label at all. In the products' favor, the freeze-dried samples held no viable microorganisms and no peptide-like impurities at the time of testing 6. A protocol built on a vial like that still cannot be evaluated, however carefully the arithmetic was done. If the vial is the largest uncontrolled variable, where it came from is the next question, and the non-US pharmacy route is covered on peptide pharmacy Europe 2026.
Link · U.S. Food and Drug AdministrationFDA alerts health care providers, compounders and patients of dosing errors associated with compounded injectable semaglutide productsThe primary document behind the unit-confusion story, including the 5 units versus 25 units case and reports of patients self-administering 5 to 20 times more than the intended dose.fda.govWhy two people get different results
Ranked by how much they explain, the ordinary causes come first and genetics comes last.
- The dose drawn, which depends on how much water went into the vial and which syringe the marks belong to. This is the largest and most correctable difference between two people who believe they are on the same protocol 2.
- What was in the vial before anyone drew from it. Purity of 7.7% to 14.37% against a 99% label claim, and endotoxin in all three vials tested, make product quality the least predictable input on the list 6.
- Injection site and depth, which change absorption speed and which the ultrasound data shows are easy to get wrong with a long needle at 90 degrees 5.
- Timing relative to food and sleep, and the pattern of delivery. The rat work on bursts against a steady trickle shows that pattern can matter independently of total amount 4.
- How long the protocol ran before anyone judged it, and against what. Lab interpretation has its own page at how to read peptide bloodwork.
- Whether the compound has ever been tested in people for the thing being asked of it. For most compounds in this category it has not, which is covered by goal on injury recovery and muscle growth.
- Genetics, last, and without a predictive claim attached.
No trial has sorted responders from non-responders by genotype for BPC-157, ipamorelin or CJC-1295. Receptor and pathway variation is real biology and it plausibly contributes, but nobody has measured it for these compounds in people, so anyone offering a genotype-based dose for a peptide is selling a number with nothing behind it. That is the same failure this page is about, arriving in a newer wrapper.
Where these compounds stand legally
Regulatory status belongs next to any dosing discussion, because it sets what the numbers can mean. Section 503A of the federal food and drug law governs which bulk substances a pharmacy may legally compound from. Under the FDA's interim policy, a substance in Category 1 may be used while the agency evaluates it, and a substance in Category 2 has been identified as raising significant safety risks and may not 10. The compound-level placements below, and the dates attached to them, are tracked with their sources on are peptides legal in the US in 2026.
| Compound | FDA status for human use | Compounding status under 503A | Prohibited in sport? |
|---|---|---|---|
| BPC-157 | Not approved for human use in the US | Placed in Category 2 in 2023, removed from Category 2 in April 2026 after the nominations behind it were withdrawn rather than because the agency judged it safe, and never moved to Category 1 12. The Pharmacy Compounding Advisory Committee recommended it for the 503A list on 23 to 24 July 2026; the FDA is not bound by that recommendation, and until the agency completes rulemaking there is no lawful compounding pathway 12 | Yes. Named under S0, non-approved substances, prohibited at all times 11 |
| Ipamorelin | Not approved for human use in the US | Not among the substances removed from Category 2 in April 2026 12, and not on the 503A bulks list 10 | Yes. Named under S2.2.1 as a growth hormone secretagogue, prohibited at all times 11 |
| CJC-1295 | Not approved for human use in the US | Not on the 503A positive list 10 | Yes. Named under S2.2.1 as a growth hormone releasing hormone analogue, prohibited at all times 11 |
| Semaglutide | The branded finished product is FDA-approved | Compounded versions are not FDA-approved products and are not reviewed for safety, effectiveness or quality 8 | Not named on the list, and not a growth hormone secretagogue 11 |




Two distinctions carry most of the confusion here. Removal from Category 2 is not permission to compound, and an advisory committee recommendation is not a rule. The full US picture, including what the 2026 Category 2 removals did and did not change, is tracked on are peptides legal in the US in 2026.
What a reader can take from this
Three of the seven rules carry a headline number that could not be traced to any document containing it: the 20-day shelf life for a mixed vial 3, the cycling calendar built on a 7-day rat study 4, and the claim that 80% of people measure under 13mm from skin to muscle 5. Two rules are sound handling with no peptide-specific number behind them, the shaking rule and the storage rule. One rule is sourced and documented, the milligram-to-unit hazard 2. One fails for a different reason: the liver enzyme genotype rests on a premise that is wrong about how peptides are cleared 7. Product quality sits outside the list entirely, and it carries the largest recorded signal of anything on this page 16. Knowing which is which is worth more than a longer checklist, because it tells a reader which rules to hold firmly and which to stop paying for.
This page's last rule says no genotype sets a peptide dose, and that applies to our own report too. What PeptidesDNA does is narrower and checkable: using the raw DNA data you already have, it ranks all 39 scored peptides by genetic match across a 144-marker panel covering 8 pharmacogenes and 15 pathways, with a human reviewing every report before it is delivered within 24 hours. It is a ranking to take to a clinician. It is not a prediction that a compound will work for you, not a diagnosis, and not a dose.
Get your DNA report- The most expensive dosing mistake is inheriting a number nobody ever checked
The 20-day shelf life for a mixed peptide vial is attributed to a bacteriostatic water label that refuses to set one, saying instead not to store reconstituted drug solutions unless the maker of that drug directs otherwise [[3]]. The cycling calendar descends from a 7-day rat study that found continuous infusion blunted growth hormone pulses and then excluded receptor downregulation and pituitary desensitization as the reason, pointing at the body's own brake instead [[4]], and no human trial tests the schedules built on top of it. For the claim that 80% of people measure under 13mm from skin to muscle, we could not find any document containing the figure, while ultrasound in 341 adults gives medians of 10.9mm to 16.9mm and specific risk estimates by needle length [[5]]. A reader who can tell a sourced rule from a repeated one is better equipped than one holding a longer checklist.
Sources12
- McCall KL, Mastro Dwyer KA, Casey RT, et al. "Safety analysis of compounded GLP-1 receptor agonists: a pharmacovigilance study using the FDA adverse event reporting system." Expert Opinion on Drug Safety 2026 Mar;25(3):581-588. FAERS 2018 to 2024, 81,078 GLP-1 reports of which 707 compounded; reporting odds ratios 48.92 [12.63, 189.6] preparation errors, 19.00 [4.24, 85.03] contamination, 8.51 [5.17, 14.0] compounding or manufacturing issues, 2.35 [1.94, 2.83] hospitalization, 0.29 [0.16, 0.53] administration errors, 0.24 [0.17, 0.32] dosing errors, 6.34 [4.32, 8.99] suicidality, 3.39 [1.61, 6.31] cholecystitis, 2.84 [2.29, 3.49] abdominal pain. The authors state the study was not designed to show a cause-and-effect relationship.
- U.S. Food and Drug Administration. "FDA Alerts Health Care Providers, Compounders and Patients of Dosing Errors Associated with Compounded Injectable Semaglutide Products." Page last updated 26 July 2024. Source of the verbatim 5 units versus 25 units case and of reports of patients administering 5 to 20 times more than the intended dose.
- Hospira, Inc. (a Pfizer company). "Bacteriostatic Water for Injection, USP" prescribing information. Contains 0.9% (9 mg/mL) or 1.1% (11 mg/mL) benzyl alcohol as a bacteriostatic preservative, is supplied in a multiple-dose container, carries the benzyl alcohol warning against use in newborns, and states verbatim: "Do not store reconstituted solutions of drugs for injection unless otherwise directed by the manufacturer of the solute." No 20-day figure appears on the label.
- Thompson NM, Davies JS, Mode A, Houston PA, Wells T. "Pattern-dependent suppression of growth hormone (GH) pulsatility by ghrelin and GH-releasing peptide-6 in moderately GH-deficient rats." Endocrinology 2003 Nov;144(11):4859-67. Seven-day infusion in rats; intermittent dosing every 3 hours augmented GH secretion and skeletal growth, continuous infusion suppressed spontaneous GH episode amplitude, and that reduction was not associated with pituitary desensitization to GH-releasing factor or down-regulation of hypothalamic GHS-R mRNA, while periventricular somatostatin mRNA rose.
- Hirsch L, Byron K, Gibney M. "Intramuscular risk at insulin injection sites: measurement of the distance from skin to muscle and rationale for shorter-length needles for subcutaneous insulin therapy." Diabetes Technology & Therapeutics 2014 Dec;16(12):867-73. Ultrasound in 341 adults; median skin-to-muscle distance 10.9mm at the thigh to 16.9mm at the buttock; estimated intramuscular risk 25% at the thigh and 9.7% at the abdomen with an 8mm needle at 90 degrees without a pinched fold, against 1.6% and 0.1% with a 4mm needle.
- Ashraf AR, Mackey TK, Vida RG, et al. "Multifactor Quality and Safety Analysis of Semaglutide Products Sold by Online Sellers Without a Prescription." Journal of Medical Internet Research 2024 Nov 7;26:e65440. Test purchases completed from 6 illegal online pharmacies; 3 injection vials delivered and 3 prefilled pens never received. Measured purity 7.7% to 14.37% against 99% claimed; semaglutide content exceeding the labeled amount by 28.56% to 38.69%; no peptide-like impurities identified; lyophilized samples devoid of viable microorganisms at the time of testing; endotoxin detected in all samples at 2.1645 to 8.9511 EU/mg.
- Solhaug V, Tveito M, Waade RB, Hoiseth G, Molden E, Smith RL. "Impact of age, sex and cytochrome P450 genotype on quetiapine and N-desalkylquetiapine serum concentrations: A study based on real-world data from 8118 patients." British Journal of Clinical Pharmacology 2023 Dec;89(12):3503-3511. States verbatim: "A significantly higher NDQ C:D ratio was observed for CYP2D6 intermediate (+7%, P = .012) and poor (+17%, P = .001) compared to normal metabolizers. No effects of CYP3A4*22 and CYP3A5*1 allele variants were observed." Concludes that females aged 65 and over carrying reduced-activity CYP2D6 variants have the highest risk of dose-dependent side effects.
- U.S. Food and Drug Administration. "FDA's Concerns with Unapproved GLP-1 Drugs Used for Weight Loss." Page last updated 1 September 2026. Reports 990 adverse event reports for compounded semaglutide and more than 730 for compounded tirzepatide as of 31 May 2026, and states that compounded products are not FDA-approved and are not reviewed for safety, effectiveness or quality.
- Liu L, Qi W, Schwartz DK, Randolph TW, Carpenter JF. "The effects of excipients on protein aggregation during agitation: an interfacial shear rheology study." Journal of Pharmaceutical Sciences 2013 Aug;102(8):2460-70. Agitation accelerated formation of protein particles at the air-water interface; polysorbate 80 substantially inhibited agitation-induced aggregation. A formulation study on a growth-factor protein, not a test of hand-shaking a peptide vial.
- U.S. Food and Drug Administration. "Bulk Drug Substances Used in Compounding Under Section 503A of the FD&C Act." Page last updated 14 May 2026. Sets out the interim policy categories: FDA does not intend to take action against a compounder using a Category 1 substance under the stated conditions, while for Category 2 substances the agency "has identified significant safety risks relating to the use of these substances in compounding pending further evaluation." The page links the current category lists; compound-level placements and dates are tracked on /learn/are-peptides-legal-us-2026.
- World Anti-Doping Agency. "Prohibited List." Current edition. Growth hormone secretagogues, including ghrelin mimetics and growth hormone releasing peptides, are prohibited at all times under section S2, and non-approved substances are prohibited at all times under section S0. Verify the current edition before competition.
- National Law Review. "Tiny chains, big changes? What FDA's latest actions mean for peptide compounding." The 2023 Category 2 placement of 19 peptide substances, the April 2026 removal after the underlying nominations were withdrawn, and why removal is not a determination of eligibility.
This article is for informational and educational purposes only. It is not medical advice and does not diagnose, treat, cure, or prevent any disease. Consult a qualified healthcare professional before starting any peptide protocol. Individual results vary. Some outbound links are affiliate links, at no extra cost to you.

Frequently asked questions
Why isn't my BPC-157 working?
The explanations worth checking first are ordinary ones: the dose drawn, which depends on how much water went into the vial and which syringe the marks belong to; injection depth, since an 8mm needle at 90 degrees without a pinched skin fold carried an estimated 9.7% chance of reaching muscle at the abdomen and 25% at the thigh in 341 ultrasound-measured adults [[5]]; how long the protocol has run before anyone judged it; and what was in the vial, given that test purchases of one peptide from online sellers without a prescription measured 7.7% to 14.37% purity against a 99% label claim [[6]]. For a protocol that worked and then stopped, an immune response to the peptide itself is its own explanation, covered on [anti-drug antibodies](/learn/anti-drug-antibodies-peptides). One more explanation belongs on the list: that it does not do what was hoped for this use. BPC-157 has no completed human efficacy trial for any indication, so an absent effect is a possible result and not necessarily a mistake in execution. Two explanations that get reached for are not supported: a liver enzyme genotype has no bearing on a peptide, which is cleared by peptidases and not by liver enzymes [[7]], and the claim that continuous use downregulates receptors traces to a rat study that excluded exactly that mechanism [[4]]. BPC-157 is not FDA-approved for human use, its published numbers are on the [BPC-157 dosage guide](/learn/bpc-157-dosage-guide), and what to change about a protocol is a question for a clinician.
How do I convert peptide milligrams to units on an insulin syringe?
The arithmetic is total milligrams in the vial divided by milliliters of water added, which gives milligrams per milliliter, and every unit on a U-100 insulin syringe is one hundredth of a milliliter. The worked examples, the calculator and the vial-size variations live on [how to reconstitute peptides](/learn/how-to-reconstitute-peptides), which owns that topic. The red flag is worth repeating in full: units are not milligrams, and the FDA has documented a provider writing 25 units for an intended 0.25 mg, producing five times the intended dose and severe vomiting, along with reports of patients self-administering 5 to 20 times more than the intended dose [[2]]. None of the compounds on this page except branded semaglutide is FDA-approved for human use, and this answer explains published arithmetic rather than recommending that anyone perform it. What to take, whether to take it, and at what dose are questions for a clinician who knows your history.
Can I use sterile water instead of bacteriostatic water, and how long does a mixed vial last in the fridge?
The difference between the two products is real, and the shelf-life numbers attached to them are not sourced. Bacteriostatic water for injection is water with 0.9% (9 mg/mL) or 1.1% (11 mg/mL) benzyl alcohol added as a preservative that holds back microbial growth, supplied in a multiple-dose container designed for repeated entry. Sterile water has no preservative and is usually single-dose [[3]]. The preservative is not a free upgrade: the label warns that bacteriostatic water is not for use in newborns because of the benzyl alcohol, and benzyl alcohol causes hypersensitivity reactions in some people, which is why the two products are not interchangeable [[3]]. On how long anything dissolved in either one lasts, the bacteriostatic water label says verbatim not to store reconstituted solutions of drugs for injection unless otherwise directed by the manufacturer of the solute [[3]]. A research peptide has no manufacturer of the solute issuing such a direction, so there is no established discard period, and the widely repeated 20-day and 3 to 5 day figures could not be traced to any document about peptides. Storage questions for a specific product belong with a clinician or pharmacist.
Why do some people respond to peptides and others do not?
The measurable differences come first: the dose drawn, what was in the vial, injection site and depth, the pattern and timing of delivery, how long the protocol ran, and whether the compound has ever been tested in people for what is being asked of it. Genetics comes last and without a predictive claim. No trial has sorted responders from non-responders by genotype for BPC-157, ipamorelin or CJC-1295. The genetic explanation people reach for most often, a slow-metabolizer liver enzyme genotype, does not apply at all: peptides are cleared by peptidases, the enzymes that cut protein chains, not by liver enzymes. In 8,118 patients taking quetiapine, a drug that genuinely is cleared by liver enzymes, reduced-function CYP2D6 variants did raise exposure to its active metabolite while CYP3A4*22 and CYP3A5*1 had no effect [[7]]. That genotype matters for that drug. It has nothing to say about a peptide.
This article is for informational and educational purposes only. It is not medical advice and does not diagnose, treat, cure, or prevent any disease. Consult a qualified healthcare professional before starting any peptide protocol. Individual results vary. Some outbound links are affiliate links, at no extra cost to you.