

There is no single best first peptide, and the useful starting question is which side of the evidence line a compound sits on. BPC-157, the compound named first in almost every starter guide, has 36 published studies behind it: 35 preclinical, meaning laboratory and non-human research done before any human trial, and one uncontrolled retrospective chart review at a single private clinic, with no clinical safety data found at all [[2]]. A 2026 structured review of injectable peptides in musculoskeletal and sports medicine found GLP-1 receptor agonists, the prescription appetite and diabetes medicines such as semaglutide, to be the only class in its scope supported by reproducible randomized evidence of symptomatic improvement in knee osteoarthritis, with that benefit driven largely by weight loss and structural cartilage change still unproven, and it placed the repair compounds and growth hormone peptides that beginner guides recommend first in the investigational column [[1]]. None of the popular research compounds (BPC-157, TB-500, GHK-Cu as an injection, ipamorelin, CJC-1295) is approved by the FDA for human use, so a beginner's first question is not which compound but which evidence tier they are willing to stand on.
BPC-157 is the compound almost every beginner guide names first. The published record behind it is 36 studies: 35 in laboratory and preclinical research, and one uncontrolled look back at 12 knees treated at a single private clinic 24. That gap between what gets recommended and what has been measured is the shape of the whole category, which is why the first useful question is not which peptide but which side of the evidence line it sits on. A 2026 structured review of injectable peptides in musculoskeletal and sports medicine put the regenerative compounds and the growth hormone peptides in the investigational column, and found only one class in its scope supported by reproducible randomized evidence: the GLP-1 receptor agonists, for symptomatic improvement in knee osteoarthritis, driven mainly by weight loss, with structural cartilage change unproven 1.
What a peptide is
A peptide is a short chain of amino acids, the same building blocks protein is made from, usually somewhere between 2 and 50 of them linked in a row. Longer chains get called proteins. The short ones mostly work as signals: they bind a receptor, which is a docking site on a cell, and the cell does something in response. Insulin is a peptide. So is the semaglutide in Ozempic and Wegovy, and the tesamorelin in Egrifta.
That is the confusing part of the category, and it is worth getting straight before anything else. Peptides as a class of medicine are old, well studied and unremarkable. The specific compounds sold online as research chemicals are a separate world that borrows the respectability of the first one. A beginner guide that blurs the two is doing you a disservice, and most of them do, because most of them exist to funnel you into a first purchase.
Which peptides have human evidence behind them?
Two 2026 reviews looked at this question from inside orthopedic and sports medicine, and they agree. The table below is the map. Read the third column before the second one, because the second column is what the marketing says and the third is what somebody actually measured in people. Two labels in the last column need a word of explanation: Category 1 is the FDA list of bulk substances a compounding pharmacy may legally prepare, and Category 2 is the list flagged as presenting significant safety risks. Being on neither list, which is where most of these sit, is not the same as being allowed 8.
| Compound or class | What beginners are told it does | What has been measured in humans | Evidence tier | US regulatory status |
|---|---|---|---|---|
| Semaglutide, tirzepatide (GLP-1 medicines) | Cuts appetite and body weight | Large randomized placebo-controlled trials support the approved weight and diabetes indications. Inside musculoskeletal medicine, a 2026 structured review found this the only class in its scope with reproducible randomized evidence of symptomatic improvement in knee osteoarthritis, mediated mainly by weight loss, with structural cartilage change unproven 1 | Approved medicine | FDA approved, prescription only. Boxed warning for thyroid C-cell tumors seen in preclinical testing, and contraindicated with a personal or family history of medullary thyroid carcinoma or MEN 2 10 |
| Tesamorelin | Raises your own growth hormone, shifts belly fat | 412 patients randomized against placebo for 26 weeks: visceral fat, the deep fat packed around the abdominal organs, fell 15.2% on tesamorelin and rose 5.0% on placebo, and IGF-1 rose 81%. Withdrawals for adverse events were more common on tesamorelin 5. It has no supporting orthopedic evidence 3 | Approved medicine for one indication, investigational for everything readers want it for. The 2026 review files it with the growth hormone secretagogues that remain investigational 1 | FDA approved for HIV-associated lipodystrophy, prescription only. Contraindicated in active malignancy and in pregnancy, raises IGF-1, and requires glucose monitoring 11 |
| BPC-157 | Heals tendons, gut and stubborn injuries | 544 articles screened, 36 included: 35 preclinical and 1 uncontrolled retrospective chart review, from which the review extracted that 7 of 12 people with chronic knee pain reported relief lasting beyond six months. No clinical safety data were found 2. It acts partly by promoting new blood vessel growth in preclinical models, so anyone with a cancer history should raise it with an oncologist before anything else 2 | Investigational | Not FDA approved. Category 2 of the 503A compounding list in 2023, removed from Category 2 in April 2026, never on Category 1 8 |
| TB-500 (a thymosin beta-4 fragment) | Whole-body repair and flexibility | Preclinical tissue-repair signals, including promoted angiogenesis, meaning new blood vessel growth, which is the reason anyone with a cancer history should raise it with an oncologist first. Human orthopedic data are lacking 3 | Investigational | Not FDA approved. Banned in sport 3 |
| GHK-Cu | Collagen, skin quality, hair | 13 patients randomized to a topical skin regimen with or without GHK-Cu after laser resurfacing. Blinded objective assessment found no significant difference in redness, wrinkles or skin quality; patient-reported satisfaction was higher (P = .04) 7. No clinical data support injected use for muscle, tendon or joint problems 3 | Investigational as an injection, small topical evidence | Not FDA approved as an injectable |
| CJC-1295 with ipamorelin | Natural growth hormone release, recovery, deeper sleep | No human efficacy trials. The supporting work is preclinical 3, and a 2026 review classes the growth hormone secretagogues, meaning compounds that prompt your own pituitary to release growth hormone, as investigational 1 | Investigational | Not FDA approved and not on the Category 1 compounding list 8 |
| Selank, Semax | Calm, focus, less anxiety | No US-registered randomized trial has been published for either. The clinical literature is small and mostly Russian-language, and both fall outside the scope of the 2026 injectable peptide reviews, which covered musculoskeletal indications 13 | Investigational | Not FDA approved in the US |
Approved medicines
The only peptides here with large randomized human trials behind them, and the only ones a US pharmacy can dispense against an ordinary prescription. Approved does not mean risk-free: each carries a label of warnings and contraindications.



Injury and tissue repair
The most-searched starters in the category, the two whose human evidence is thinnest, and both act partly by promoting new blood vessel growth in preclinical models. Anyone with a cancer history should raise that with an oncologist before considering either.


Skin and visible aging
The published human work on GHK-Cu is topical skin research, which matters a great deal when it is sold as an injection.
Growth hormone axis
Compounds that prompt your own pituitary instead of supplying growth hormone. Sermorelin is the only one of the three with a current US compounding pathway.



Mood and focus
Fast-acting on paper, and almost entirely untested in registered Western trials.


Gut and immune
Narrow, specific uses rather than general starting points.


Injectable peptides for sports medicine remain largely experimental. Clinical use should be confined to approved metabolic agents for indicated conditions and to rigorously designed research protocols.Villegas Meza AD et al., JBJS Reviews, 2026
The second 2026 review, a primer written for orthopedic surgeons whose patients keep arriving with peptides already in the fridge, went compound by compound and reached the same place. Its authors describe the single human BPC-157 case series as carrying significant methodological flaws and a lack of controls, and close by writing that "information regarding the indications, dosing, frequency, and duration of treatment remains unknown" 3. That sentence is the state of the field, and it is why this page states no dose figures of its own. The compound monographs at BPC-157 and TB-500 carry the full evidence detail, and the dosage guides such as the BPC-157 dosage guide document the ranges that published studies and practitioner protocols report. Those are a record of what has been used, not a recommendation to you, and no trial has established a dose for any of the investigational compounds here 3.
How long did the published studies run?
A beginner reading forums gets a wildly compressed sense of timing, so it helps to see when the published work measured anything at all.
| Study | Design and size | Endpoint measured at | What it found |
|---|---|---|---|
| Tesamorelin in HIV-associated fat accumulation 5 | Randomized, placebo controlled, 412 patients | 26 weeks | Visceral fat down 15.2% versus up 5.0% on placebo. Withdrawals for adverse events were more common on tesamorelin |
| Topical GHK-Cu after laser skin resurfacing 7 | Randomized, 13 patients completed | 12 weeks | No significant objective difference in redness, wrinkles or skin quality. Patient satisfaction was higher on GHK-Cu |
| BPC-157 injected into the knee 4 | Retrospective chart review and telephone survey at one private clinic, uncontrolled, 17 patients of whom 16 were reached | Relief reported beyond 6 months | The systematic review extracted 7 of 12 patients reporting lasting relief. No control group, no blinding, no randomization 2 |
Why are peptides injected rather than swallowed?
Because the digestive system is built to take protein apart, and a peptide is a short piece of protein. The gut does not distinguish between the chicken you ate and the compound you paid for.
What happens to a swallowed peptide
Swallowed peptides deliver under 1% of the dose into the blood. Injection bypasses the gut entirely. That gap is why the needle exists.
A capsule of something normally injected only works if it carries an absorption enhancer with published pharmacokinetic data behind it 6. Without that, almost none of the dose reaches the blood. The full account of the barriers, and which compounds have genuine non-injected routes, lives at oral peptide bioavailability, which owns that topic.
The decision that comes before the compound
The same molecule bought two ways is two different risk propositions, and almost every downstream beginner question resolves differently depending on which side of this line you are standing on.
Two routes to the same vial
How to vet a clinic and the pharmacy behind it
Peptide clinics vary enormously, and the difference is visible from the first phone call. Two terms will help before you make it. A 503A pharmacy compounds one prescription for one named patient under state pharmacy board oversight. A 503B outsourcing facility is registered with the FDA and makes batches under federal manufacturing standards, with more inspection behind it. A clinic that cannot tell you which kind of facility makes its product has already told you something. All of this is the US picture, and if you are in Europe the pharmacy route and the legal position are different: the European pharmacy picture covers that.
The legal rule underneath it is narrower than most clinics admit. Under Section 503A a pharmacy may compound from a bulk substance only if that substance has a USP or NF monograph, is a component of an FDA-approved drug, or appears on the FDA 503A bulks list. BPC-157 meets none of the three 8. A prescriber who describes it as "pharmacy grade" without explaining that is either uninformed or hoping you are. Sermorelin is on Category 1 of that list, which is why sermorelin is the one growth hormone axis peptide a US pharmacy can legally compound 8.
- Do you require blood work before prescribing anything, and what does that panel cover?
- Which facility makes your product, is it a 503A pharmacy or a 503B outsourcing facility, and can you name it?
- Will you show me a certificate of analysis whose batch number matches the vial I receive?
- What is the re-check schedule, which markers do you re-draw, and at what interval?
- What are your stop criteria, meaning what would make you take me off this?
The baseline you take before day one
Almost nobody starting out does bloodwork first, and one draw costs less than a single vial. Without a before, you are comparing how you feel now against how you remember feeling, which is unreliable in both directions and biased toward whatever you paid for.
The panel people usually discuss with a doctor before starting anything covers a full blood count, a metabolic panel including liver and kidney markers, a lipid panel, and fasting glucose with HbA1c, which is a three-month average of blood sugar. Thyroid function often comes with it. If the growth hormone axis is the goal, IGF-1, the blood marker that rises when growth hormone rises and the number those compounds are actually judged by, is the downstream marker that pathway moves, and when you draw it changes what it says. What each marker means belongs to how to read peptide bloodwork, and the timing question specifically to IGF-1 blood test timing. Interpreting any of it is a conversation with a doctor, because a result that means nothing in one person means something in another.
A baseline you never needed costs one blood draw. Not having one when you do need it costs you the ability to know what changed.
It arrived as a powder. What now?
A vial turns up holding a small amount of white powder and nothing about it explains the next step. Three details do most of the work, and each has a page here that owns it.
The liquid is bacteriostatic water, which is sterile water holding a small amount of benzyl alcohol so the vial stays usable for weeks after the first needle goes in. Plain sterile water does not do that, which is why it is the wrong choice for a multi-dose vial. The water goes down the inside wall of the vial rather than straight onto the powder, and then you swirl it until it dissolves. You do not shake it: agitation can shear the molecule, and a peptide that has been shaken apart looks exactly like one that has not.
The detail that trips up more beginners than any other is concentration. How much water you add changes nothing about how much compound is in the vial, only how concentrated it is. Two people following the same written protocol can inject amounts that differ several-fold and both believe they followed it. The peptide calculator does the arithmetic; how to reconstitute peptides and the common dosing mistakes carry the rest.
Where the needle goes, and what is not normal
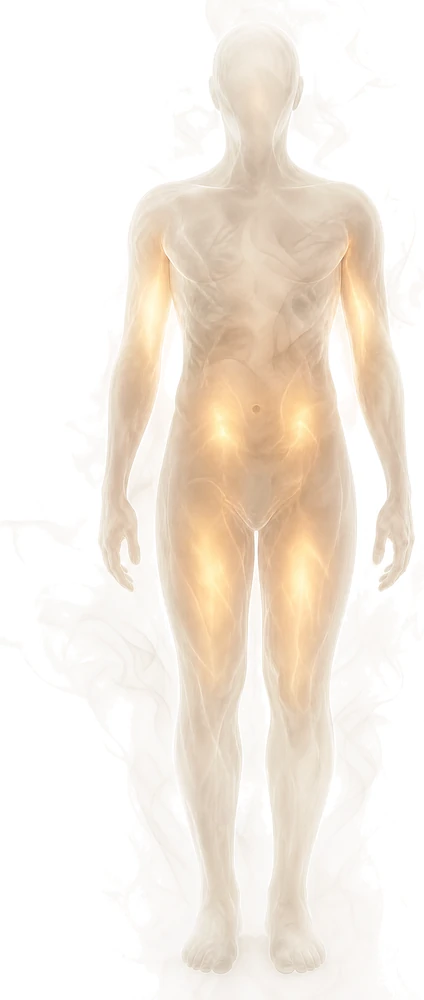
These are subcutaneous injections, meaning into the layer of fat just under the skin rather than into muscle, and the usual sites are the abdomen away from the navel, the front or outer thigh, and the back of the upper arm. Technique, site rotation and sterile practice belong to the peptide injection hygiene guide, which covers all of it properly.
Subcutaneous sites
- AbdomenThe usual first choice. Stay roughly two finger-widths clear of the navel.
- Front or outer thighEasy to reach and easy to see what you are doing.
- Back of the upper armThe fleshy part at the back. Awkward to self-inject.
How do you know what is in the vial?
This is the largest practical risk a beginner runs, larger than the molecule itself, and the 2026 and 2025 reviews say so explicitly 12. Nothing about a research-chemical vial has been checked by a regulator: not the identity of the contents, not the amount, not what else is in there. Independent testing of gray-market vials has repeatedly turned up products that fail identity, purity or endotoxin checks, and because no regulator verifies them, the failure rate in any given batch is unknown.
Adverse effects are possible due to unregulated manufacturing, contamination, or unknown clinical safety.
Four things separate a serious vendor from a bad one, and all four are documents rather than promises. A certificate of analysis, usually written COA, is a lab report on what is in the product, and the word that matters is batch: the batch number printed on the certificate should match the batch number on the vial you were sent. One undated certificate covering an entire catalog tells you nothing. HPLC purity, short for high performance liquid chromatography, separates out everything in a sample and measures the proportions, so it answers how much of this is the thing I ordered. Mass spectrometry answers a different question, which is whether the molecule is the right molecule at all. Endotoxin testing, sometimes listed as LAL, checks for bacterial residue left behind during manufacture.
Consistent warning signs: prices well below everybody else, no batch numbers anywhere, certificates with no laboratory named, health claims attached to a product sold legally for research only, and a vendor who answers a direct question about testing with marketing copy instead of a PDF.
What it costs, without a number we cannot stand behind
Two points about money, and no price quotes, because prices in this market move constantly and we have not run a survey we could cite.
- The number that matters is cost per dose, not cost per vial, and it depends entirely on how many doses a vial yields at whatever dilution you use. A cheap vial that empties in two weeks costs more per dose than an expensive one that lasts two months. The peptide calculator will tell you how many doses a vial holds.
- The route changes the total far more than the compound does. The prescription route costs materially more because you are paying for a prescriber, a pharmacy that answers for its product, and a supply chain with a name attached, and these protocols are almost never covered by insurance.
- Budget for the consumables. Bacteriostatic water, syringes, alcohol wipes and a sharps container are a real line item that people forget.
The compound is the cheap part of this. Accountability is the expensive part, and it is the part you are actually choosing between.
What a stack is, and why it is the wrong place to start
A stack is more than one peptide taken together, on the theory that different jobs add up. Some are mixed by the person taking them and some are sold pre-mixed in a single vial, which matters more than it sounds: a pre-mixed blend can put four compounds into you when you have read about one. The other thing to see before you buy one is that a blend is almost never equal parts. The cards below draw each member vial proportional to how much of it the blend actually contains.

Healing and repair
Wolverine Stack
10 mg vialThe two repair peptides people pair for injuries

Skin and appearance
KLOW
80 mg vialGLOW with an anti-inflammatory peptide added
For a beginner, a stack destroys the only information you were going to get. Take three things at once and something happens, good or bad, and you have no way of knowing which one did it. One compound at a time is slower and tells you far more. If the Wolverine stack is the thing that brought you here, our review of it is the unvarnished version. When stacking does become the right question, peptide stacking 101 covers the rules and how to build a peptide stack covers construction.
What the first weeks and months look like
The most common way a beginner wastes money is quitting before a compound could possibly have worked, or deciding one works after three days when the real cause was a good week of sleep. Categories run on different clocks, and knowing which clock you are on is most of the discipline.
- Days 1 to 14: the fast categoryMood and focus compounds such as Selank and Semax act on signaling that shifts quickly, and people who notice anything usually notice within hours to days. Two weeks of consistent use with nothing at all is real information. The published clinical literature behind both is small and has not been replicated in registered Western trials, so a null result is not surprising.
- Weeks 2 to 8: the repair categoryTendon and soft tissue do not turn around in days, so judging a repair compound at two weeks is judging it before the question has been asked. This category also carries the worst confound: injuries improve on their own, and by week six you cannot separate the compound from time, rest and the fact that you stopped doing the thing that hurt.
- Weeks 4 to 26: the growth hormone categoryChanges in body composition through the growth hormone axis are gradual by design. The randomized tesamorelin trial, which used an approved medicine at a known dose in 412 people, measured its primary endpoint at 26 weeks.
Start a compound, change your training and add a supplement in the same week, and you have learned nothing regardless of what happens next. One compound, one goal, long enough for that category's clock to run, and a written note of where you actually were on day one: which movements hurt, how much, how you slept. Judging whether something worked, and the question of time on and time off, belong to the peptide cycling protocol. If a response fades after months instead of never arriving at all, anti-drug antibodies covers why that happens.
Why the same vial does different things to two people
Before genetics, run through the ordinary explanations, because they account for most of the variation and they are all cheaper to check. The dose, which depends on how the vial was diluted. The product itself, which may not contain what the label claims. Whether the problem was ever the kind of problem the compound addresses, which is the most common quiet failure. Time, since the category clock may not have run. And everything else in the person's life: sleep, training load, age, other medicines, and what else they started the same week.
Then genetics. No published trial has sorted responders from non-responders by genotype for any of the research compounds on this page, so nobody can tell you from a DNA file whether BPC-157 will work for you, and anybody who says otherwise is describing a study that does not exist. What genetic data can contribute is background on the pathways a compound acts through, and ordering: a way to decide which two or three of forty candidates are worth reading about first, before you have spent anything. There is also a real limit on what consumer files can read, which matters when you are shopping for reports. Array data cannot resolve CYP2D6, CYP3A4, CYP1A2 or CYP2E1, the liver enzymes that break down most medicines, so a service promising a full liver-enzyme readout from a 23andMe file is promising something the file does not contain.
Use genetic data to narrow a shortlist before you spend money, and treat a friend's result as weak evidence about you. How we score, and what the 144-marker panel weighs, is written up at our methodology, which is the thing to read before you pay anybody, us included, for a genetic report. If you already have a raw data file, the 23andMe peptide guide covers what to do with it and the DNA decision framework covers how to use it to choose. If you are over 50, peptides after 50 is the age-specific version of this orientation.
Where this sits legally, and in sport
The regulatory picture moved in 2026, and it moved in the opposite direction to how most forums describe it.
- 2023: Category 2The FDA placed BPC-157 in Category 2 of the 503A bulk drug substances list, the list flagged as presenting significant safety risks, which barred US compounding pharmacies from preparing it.
- April 2026: removed from Category 2The nominations behind that listing were withdrawn and BPC-157 came off Category 2. Removal deleted a prohibition without creating an authorization, and the compound has never been on Category 1.
- July 2026: advisory committee reviewThe FDA's Pharmacy Compounding Advisory Committee, the outside panel that advises the agency on which substances pharmacies may use, met on 23 and 24 July 2026 to review BPC-157 and six other compounds for Category 1 placement. Even a favorable recommendation is non-binding: the FDA must agree, and rulemaking follows, which takes more than a year.
So there is still no legal US compounding pathway for BPC-157 89. The full picture, including import rules and who actually carries legal risk, is at are peptides legal in the US in 2026, which owns that topic.
Sport is simpler and stricter. BPC-157 is banned in professional sport 2, TB-500 and its parent thymosin beta-4 are banned substances in sport 3, and the 2026 review describes widespread antidoping restrictions across the regenerative peptides and growth hormone secretagogues as a group 1. A prescription is not a defense, and neither is a vial labeled for research.
What to do this week
- Name one goal and one way you would measure it, written down today. If the goal is your starting point rather than a compound, the goal pages are the better door: injury recovery, weight loss, sleep, anxiety or anti-aging.
- Look your candidate compound up in the evidence table above and decide whether you are comfortable with the tier it sits in. If the honest answer is no, you have saved yourself money and a needle.
- Book a baseline blood panel and a conversation with a doctor who will discuss this rather than end it. Ask the five questions above if a clinic is involved, and raise any cancer history before anything that promotes new blood vessel growth.
- Understand what the research-vial route asks of you before you consider it. No regulator has checked the identity, the amount or the sterility of what is in that vial, so verification is entirely yours: a batch-matched certificate of analysis, HPLC purity, mass spectrometry identity and endotoxin testing, all four, all documents. For many people that burden is the reason to stop here. If you want to see how vendors compare on those documents, our vendor comparisons carry the affiliate links disclosed at the top of this page.
- If you and a clinician decide to proceed, give it the clock its category runs on, change one variable at a time, and write down how it started so week eight has something to compare against.
Every mechanic on this page is documented in more detail elsewhere on the site. The evidence question is the one that stays open, so take it into any conversation with a prescriber: how many people has this been tested in, and what did the trial measure?
Curious how your own genes shape the pathways these compounds act on? Upload the raw DNA data you already have from 23andMe, AncestryDNA or MyHeritage, and get all 39 peptides ranked against a 144-marker panel covering 8 pharmacogenes and 15 pathways. Results come back within 24 hours, after a human reviews them. This is an educational genetic-interpretation report. It is not a diagnostic test, it does not predict whether any compound will work for you, and it is not a substitute for medical care.
Get your DNA report- The beginner ladder is upside down
The compounds sold to beginners as the sensible first step are the ones with the least human evidence, and the peptides with real randomized human trials behind them are prescription medicines that almost nobody thinks of as peptides. That inversion is why evidence tier decides what a starting dose, a known side effect profile and accountability even mean.
Sources12
- Villegas Meza AD, Nocek M, Mitchell BC, et al. Injectable Peptides in Sports Medicine: A Structured Narrative Review of Evidence, Safety, and Antidoping Implications. JBJS Reviews 2026;14(5)
- Vasireddi N, Hahamyan H, Salata MJ, et al. Emerging Use of BPC-157 in Orthopaedic Sports Medicine: A Systematic Review. HSS Journal 2025;21(4):485-495
- Mayfield CK, Bolia IK, Feingold CL, et al. Injectable Peptide Therapy: A Primer for Orthopaedic and Sports Medicine Physicians. American Journal of Sports Medicine 2026;54(1):223-229
- Lee E, Padgett B. Intra-Articular Injection of BPC 157 for Multiple Types of Knee Pain. Alternative Therapies in Health and Medicine 2021
- Falutz J, Allas S, Blot K, et al. Metabolic effects of a growth hormone-releasing factor in patients with HIV. New England Journal of Medicine 2007;357(23):2359-2370
- Vahora S, Shah V, Patel B. Semaglutide Bioavailability: Limitations, Formulation Innovation and Future Opportunities. Pharmaceutical Research 2026
- Miller TR, Wagner JD, Baack BR, Eisbach KJ. Effects of topical copper tripeptide complex on CO2 laser-resurfaced skin. Archives of Facial Plastic Surgery 2006;8(4):252-259
- US FDA. Certain Bulk Drug Substances for Use in Compounding That May Present Significant Safety Risks (503A Category 1 and Category 2 lists)
- US FDA. Pharmacy Compounding Advisory Committee (meeting materials and schedule, including the July 23-24 2026 meeting on 503A bulk drug substances)
- Novo Nordisk. WEGOVY (semaglutide) injection and tablets, US prescribing information, June 2026. DailyMed, US National Library of Medicine
- Theratechnologies. EGRIFTA WR (tesamorelin) for injection, US prescribing information, August 2026. DailyMed, US National Library of Medicine
- US FDA. FDA alerts health care providers, compounders and patients of dosing errors associated with compounded injectable semaglutide products (2024)
This article is for informational and educational purposes only. It is not medical advice and does not diagnose, treat, cure, or prevent any disease. Consult a qualified healthcare professional before starting any peptide protocol. Individual results vary. Some outbound links are affiliate links, at no extra cost to you.

Frequently asked questions
What are peptides, for somebody starting from zero?
A peptide is a short chain of amino acids, the same building blocks protein is made from, usually 2 to 50 of them. Most work as signals: they bind a docking site on a cell and the cell responds. The category splits in two, and that split matters more than anything else a beginner learns. Some peptides are approved medicines with large randomized trials behind them, such as semaglutide, tirzepatide and tesamorelin. Others, including BPC-157, TB-500, GHK-Cu as an injection, ipamorelin and CJC-1295, are sold as research chemicals, are not approved by the FDA for human use, and are supported mostly by laboratory and preclinical research [[1]].
What is the best peptide for beginners?
There is no universal best first peptide, and the compounds recommended most often to beginners are the ones with the least human evidence. A 2026 structured review of injectable peptides in musculoskeletal and sports medicine found GLP-1 receptor agonists to be the only class in its scope supported by reproducible randomized evidence of symptomatic improvement in knee osteoarthritis, mediated mainly by weight loss, and it placed the repair compounds and growth hormone peptides in the investigational column [[1]]. BPC-157, the usual recommendation, has 35 preclinical studies and one uncontrolled retrospective chart review behind it, from which 7 of 12 people with chronic knee pain reported lasting relief [[2]][[4]]. The useful first move is choosing a supply route and a clinician, then matching one compound to one goal with a doctor who knows your history.
Are peptides safe for beginners?
Safety is unknown for most of them rather than established. The 2025 systematic review of BPC-157 states plainly that no clinical safety data were found, and attributes the realistic risk to unregulated manufacturing and contamination rather than to the molecule [[2]]. The documented harm in this space is largely procedural: the FDA has reports of people self-administering 5 to 20 times the intended dose of compounded injectable semaglutide after confusing milliliters, milligrams and syringe units, with some hospitalized [[12]]. The approved medicines are not risk-free either, they are simply documented: semaglutide carries a boxed warning about thyroid C-cell tumors seen in preclinical testing and is contraindicated with a personal or family history of medullary thyroid carcinoma or MEN 2 [[10]], and tesamorelin is contraindicated in active malignancy and in pregnancy [[11]]. Research compounds have no equivalent document.
Do you need a prescription for peptides?
It depends which peptide. Semaglutide, tirzepatide and tesamorelin are FDA-approved medicines and require a prescription. BPC-157, TB-500, GHK-Cu, ipamorelin and CJC-1295 are not approved for human use, and for most of them there is no legal US compounding pathway either. Under Section 503A a pharmacy may compound from a bulk substance only if it has a USP or NF monograph, is a component of an FDA-approved drug, or appears on the FDA 503A bulks list, and BPC-157 meets none of the three [[8]]. Sermorelin is on Category 1 of that list, making it the one growth hormone axis peptide a US pharmacy can compound. Vials sold online labeled for research use only are not a prescription-free version of a medicine; that label is doing real legal work. [Are peptides legal in the US in 2026](/learn/are-peptides-legal-us-2026) covers the detail.
How long does it take for peptides to work?
The category matters far more than the individual compound. Mood and focus compounds act on signaling that shifts within hours to days, repair compounds work on the timescale tendon and soft tissue heal on, meaning weeks rather than days, and growth hormone axis changes run in months: the randomized tesamorelin trial measured its primary endpoint at 26 weeks [[5]]. The confound to know about is that injuries improve on their own, so at week six you cannot separate the compound from time and rest unless you wrote down where you started. No trial has predicted response speed from anybody's genotype for any of these compounds.
This article is for informational and educational purposes only. It is not medical advice and does not diagnose, treat, cure, or prevent any disease. Consult a qualified healthcare professional before starting any peptide protocol. Individual results vary. Some outbound links are affiliate links, at no extra cost to you.